Top 10 claim denials in medical billing (and how to prevent each one)

Most denial workflows are built to fight claims after they're rejected, but the highest-return work in the revenue cycle happens earlier: Preventing denials before they start. This guide breaks down the ten most common types of denials and shows you how to deploy prevention strategies to stop revenue loss at the source. 

Denial prevention strategies to curb $43 billion in hospital payment recovery costs 

In 2025, U.S. hospitals spent more than $43 billion trying to collect payments for care they had already delivered, according to the American Hospital Association. That is the price of chasing money you already earned, and it keeps rising as denials are increasing across nearly every payer. 

A large share of those denials is administrative and avoidable.  

When the root cause is a missing authorization or an eligibility error, the fix belongs upstream, at registration and pre-bill review rather than in an appeal queue months later. 

Denials driven by front-end and process errors are winnable when you move resources toward preventing them instead of reworking them. The ten categories below are where that shift pays off fastest. 


top 10 denials in medical billing


1. Prior authorization failures

What it is: These denials hit when a service required prior authorization, and that approval was either missing or didn't match the procedure performed. 

Why it happens: Most trace back to a simple sequencing problem. The authorization was never secured before the service, or the payer approved one CPT while the clinician performed another. Approvals that lapse before the date of service create the same result. 

How to prevent it: Confirm the authorization covers the exact CPT you plan to bill and is still active on the date of service.  

Re-check any time the procedure or the plan changes after the initial sign-off. A payer-specific requirement matrix helps schedulers flag which services need authorization for which plans before anything gets booked. 

These denials are also among the most recoverable, so the ones that slip through are worth pursuing.  

KFF found that only 11.5% of denied Medicare Advantage prior-authorization requests were appealed in 2024, and 80.7% of those appeals succeeded.

2. Patient eligibility and coverage issues

What it is: The patient's coverage was inactive on the date of service, or the plan details on the claim didn't match the payer's records. 

Why it happens: Eligibility gets checked once at scheduling and never confirmed again, so a coverage change before the visit goes unnoticed. Simple transcription errors in the member ID or date of birth produce the same rejection. 

How to prevent it: Run real-time eligibility at scheduling and again at check-in, and verify plan-specific benefits rather than a simple active or inactive status.  

Confirm the member ID and date of birth against the card at registration so a typo never reaches the payer. Re-verify whenever coverage could have shifted, such as a new plan year or a job change, since those transitions are where stale eligibility data does the most damage. 

3. Medical necessity denials

What it is: The payer agrees that the service happened but decides that the documentation didn't justify it as medically necessary for the diagnosis submitted. 

Why it happens: The clinical documentation doesn't meet the criteria in the payer's Local Coverage Determination (LCD), National Coverage Determination (NCD), or medical policy. Even when the service was appropriate, the record may not demonstrate the diagnosis, severity, or failed conservative treatment the payer requires to consider it medically necessary. 

How to prevent it: Check the payer's medical policy and the applicable LCD or NCD before delivering any scheduled service, and code to the full ICD-10 specificity that supports necessity.  

Build concurrent clinical documentation review into the encounter so gaps get closed while the patient is still in-house, when documentation is easiest to correct. For traditional/fee-for-service Medicare claims likely to fail a necessity test, issue an ABN so the balance stays billable to the patient. 

Medical necessity denials are among the most contested, and payers reverse a large share of them on appeal. One Health Affairs analysis found Medicare Advantage plans denied roughly 17% of claims, with 57% ultimately overturned.  

Prevention keeps those cases out of the appeal queue in the first place. 

4. Incomplete or insufficient clinical documentation

What it is: This denial comes when the medical record doesn't fully support the services or diagnoses on the claim. 

Why it happens: Documentation is written for clinical care first, so the billing-critical details often go missing. A note may lack the specificity a code requires, or it may arrive unsigned or too late to support timely billing. 

How to prevent it: Give clinicians documentation templates tied to your highest-risk diagnoses so the required elements get captured the first time. Showing physicians exactly how their wording affects reimbursement and audit exposure is one of the most effective ways to close gaps before they turn into denials. 

Move clinical documentation integrity upstream by querying physicians during the encounter, while the care is fresh and the record can still be corrected.  

5. Coding errors (ICD-10, CPT, HCPCS)

What it is: Codes that are outdated or that don't match the documentation and the other codes on the claim. 

Why it happens: A diagnosis code lacks specificity, or a code set changes and the old value keeps getting applied. CMS revises ICD-10 every fiscal year, so last year's correct code can quietly become this year's denial. 

How to prevent it: Run automated coding edits before the claim drops and code to the highest specificity the record supports.  

Schedule annual coder and CDI training on the IPPS final rule and the yearly ICD-10 and CPT updates so changes get caught at the source.  

Regular coding audits against national benchmarks surface the patterns worth fixing before a payer finds them. 

6. Non-covered or excluded services

What it is: The service isn't a covered benefit under the patient's specific plan. 

Why it happens: Usually a benefit exclusion or a plan limit, such as a capped number of visits per year or a service the plan treats as experimental. Coverage also varies widely by payer program, so a service covered under one plan can be excluded under another. 

How to prevent it: Verify covered benefits and any coverage limits before the service, and capture patient liability with an ABN or advance notice of non-coverage when a service falls outside the plan.  

Flag plan-specific exclusions during scheduling so patients can weigh financial responsibility ahead of time.  

Payer-specific programs carry their own coverage rules, and understanding why VA hospital claims are rejected helps teams anticipate exclusions that standard commercial logic would miss. 

7. Timely filing and late submission

What it is: The claim simply arrived after the payer's filing deadline. This is one of the most preventable types of denials.  

Why it happens: Deadlines vary widely, from 90 days to a full year, and each payer counts from its own starting point. A clean claim that stalls in internal review or bounces back for a minor error can burn through the window before anyone notices. 

How to prevent it: Track each payer's filing clock from the date of service and set automated aging alerts well before the deadline.  

Prioritize first-pass claim accuracy so rework doesn't eat the remaining days.  

For any claim that stalls internally, build an escalation trigger that surfaces it while there is still time to file. 

8. Coordination of benefits (COB) errors

What it is: The payer believes another insurer should have paid first, or the primary and secondary order on the claim is wrong. 

Why it happens: Patients with more than one active plan are the usual trigger. When the payment order is unclear or the primary payer's information is missing, the secondary payer rejects the claim until the sequence gets resolved. 

How to prevent it: Confirm the primary and secondary payer order at registration and re-verify it any time coverage changes.  

Attach the primary payer's EOB to the secondary claim so the payment sequence is documented on submission. Some payers have also begun requiring proof that the primary was billed within its filing limit, so fold that documentation into your secondary-claim workflow. 

9. Bundling and unbundling errors

What it is: These denials come from how procedure codes are combined, either bundling services that should be billed together or unbundling ones that shouldn't be split. 

Why it happens: Most are caught by the National Correct Coding Initiative (NCCI) edits, which compare code pairs billed for the same patient on the same day and deny one of them when the pairing breaks the rules. NCCI edits apply to professional claims, while facility and outpatient hospital claims are governed by the Outpatient Code Editor (OCE). Improper unbundling commonly triggers a CO-97 denial and can invite a payer audit. 

How to prevent it: Apply NCCI edits before the claim goes out and use modifiers only when the documentation clearly supports separate billing.  

Audit your highest-volume code pairs regularly, so recurring errors get corrected at the template level.  

When a modifier is in question, confirm the record justifies it before submission. 

10. Payer policy changes and AI-driven algorithmic denials

What it is: Payers update coverage rules or run claims through automated algorithms that reject them in seconds. 

Why it happens: Payers increasingly use AI to review claims at a speed and scale no manual team can match. A Stanford-led review in Health Affairs described the dynamic as an "arms race," and an NAIC survey of 93 large insurers found 84% already use AI in their operations. Automated denials often apply rigid criteria without weighing a patient's clinical circumstances. 

How to prevent it: Monitor payer policy bulletins and track denial patterns by payer and denial type so you can spot algorithmic behavior early.  

When a denial originates from an algorithm rather than a clinical reviewer, frame the appeal around the criteria the system overlooked. Denial patterns also vary sharply by payer. Understanding why Medicaid MCO denials exceed Medicare Advantage helps teams direct effort where the risk runs highest. 

Note: Under CMS-4208-F, effective January 1, 2026, once a Medicare Advantage plan approves an inpatient admission it generally cannot reverse that approval based on information gathered afterward. Teams unaware of this protection may concede reversals they no longer have to accept. 

How EnableComp can help 

EnableComp's denial management suite pairs specialized analytics with clinical and billing expertise to resolve complex denials that slip through standard revenue cycle workflows.

Instead of working every denial the same way, EnableComp uses systematic detection logic to surface high-risk claims and root-cause patterns at scale, paired with a prevention workflow built around payer-specific rules and timely filing requirements. 

Schedule a consultation to see how much revenue you're leaving behind.  


 _____________

About the author 

Kelsey Taylor, BSN, RN, is the Senior Director of Clinical Denials at EnableComp, bringing over 10 years of experience in healthcare management and clinical operations to the role. Her background spans clinical quality, care management, and product management, giving her a well-rounded lens on how revenue cycle, training, and clinical operations intersect. She’s passionate about empowering teams to deliver patient-centered, impactful results and frequently speaks on topics like DRG revenue integrity, complex revenue recovery, and denial prevention strategy. 


The Federal IDR Final Rule changed which disputes are worth filing. Here's what to do first.

For three years, your federal IDR (Independent Dispute Resolution) strategy has been governed by a single, quiet constraint: The arbitration fee was so high that thousands of legitimate out-of-network (OON) claims were never worth disputing.  

That math just changed overnight, and the service lines you wrote off as uneconomical are back in play. This guide shows you exactly what the new Federal IDR Operations Final Rule (CMS-9897-F) changes, why it changes your threshold economics, and the specific steps to take before the fee reduction takes effect. 

How much did the IDR administrative fee decrease? 

The per-party administrative fee for a federal IDR dispute falls from $115 to $15 – an 87% reduction.  

The Departments estimate this reduction from $115 to $15 transfers roughly $504 million annually back to disputing parties. 

That $115 fee existed because the IDR process was drowning. Since launching in April 2022, the system has received more than 5 million disputes,  a volume that vastly exceeded the Departments' original projections and created the backlogs that made a high fee feel necessary. The fee was a rationing tool, and it worked by pricing your smaller claims out of the process entirely. 

Now consider what that meant in practice. At $115 per party, a single low-dollar anesthesia or radiology claim rarely cleared the breakeven line. The fee alone consumed most of the expected recovery. So those claims never entered the queue, not because they lacked merit, but because the arithmetic said no.  

How does the fee reduction change IDR dispute economics? 

Here is the mechanism that matters. Your IDR threshold model is a function of three variables: the administrative fee, the certified IDR entity fee, and your expected recovery net of internal labor. When the administrative fee drops 87%, the breakeven point for a viable dispute drops with it. 

The rule compounds this with a second change: Batching capacity expands from 25 to 50 qualified items per dispute.  

More lines per dispute means the fixed cost of arbitration spreads across twice the claim value. Per-line dispute cost falls on both axes at once. 

Most revenue cycle teams built their "is this worth disputing?" logic when the fee was $115. That logic now excludes claims that have become clearly profitable to pursue. The Departments themselves project a 30% increase in dispute volume driven by exactly this incentive shift. 

There's real money at stake in getting this right. Providers have historically prevailed in a strong majority of IDR disputes, with awards averaging well above the median in-network rate.  

Hospitals spent an estimated $5 billion cumulatively on IDR-related expenses from 2022 through 2024, per Congressional Research Service analysis (Report R48851). The rule doesn't just lower a fee,  it changes the return on a large, existing cost center. 

The key provisions at a glance 

Keep this table close as you brief your team. These are the operational levers the rule pulls. 

Provision

Detail 

Administrative          fee reduction  $115 to $15 per party per dispute, regardless of dispute amount or eligibility outcome. Departments estimate approximately $504 million annually transferred back to disputing parties. Effective five business days after Federal Register publication. 


Batching expansion  Up to 50 qualified IDR items and services per dispute (up from 25). Three permitted configurations: single-patient encounter; same or comparable code across one or more patients; same Category I CPT code range for anesthesia, radiology, pathology, and laboratory services. 


CARC / RARC standardization  Plans and issuers must use specified Claim Adjustment Reason Codes and Remittance Advice Remark Codes on OON remittance. Codes will communicate No Surprises Act (NSA)  scope and IDR eligibility. Code guidance anticipated within six months of publication; applicability no less than four months after guidance. 


Federal IDR Registry  Self-insured plans, health insurance issuers, and FEHB Program carriers must register with the Departments and receive permanent registration numbers – addressing the persistent problem of counterparty identification in OON disputes. 


Open negotiation reforms  Standardized notice form, mandatory portal transmission, mandatory 15-business-day response, timing clarified in business days. 


IDR initiation & eligibility  New attestation requirements at initiation; non-initiating party must furnish supporting documentation for eligibility objections; certified IDR entities determine eligibility within five business days. 


IDR Gateway platform  New centralized platform for dispute initiation, tracking, and management. Phased rollout beginning 2026; full functionality anticipated within 24 months of rule effective date. 


What should providers do now that the IDR fee has changed? 

The $15 fee applies to disputes initiated five business days after Federal Register publication, and the rule itself is effective August 3, 2026. The operational changes phase in on a rolling basis after that. That gives you a narrow planning window, not a long one. Focus here: 

1. Rebuild your threshold ROI models by specialty and service code. Any model built on a $115 fee is now wrong in the direction that costs you money. Rerun the breakeven using the $15 fee and 50-item batching capacity. Where the old rule was "dispute if expected recovery exceeds roughly $X," recalculate X for each high-volume, lower-dollar service line – anesthesia, radiology, pathology, and laboratory first, since those are where the batching configurations and the fee drop combine most powerfully. 

2. Build a batching strategy aligned to the three permitted groupings. The rule permits three configurations: a single-patient encounter; the same or comparable code across one or more patients; and the same Category I CPT code range for anesthesia, radiology, pathology, and laboratory. Map your OON denial inventory to these groupings now. The teams that pre-sort their claims into valid batches will file faster and cheaper than teams batching ad hoc. 

3. Tighten intake and eligibility screening. The rule raises the bar for a properly initiated dispute. There are new attestation requirements at initiation, and certified IDR entities now determine eligibility within five business days. If your intake process lets weak disputes through, you'll burn that fast eligibility clock on claims that were never going to qualify. Screen harder at the front so your filings hold up. 

4. Prepare your remittance tooling for CARC/RARC ingestion. Once code guidance publishes and becomes applicable, plans must use standardized codes on OON remittance to signal NSA scope and IDR eligibility. The Departments estimate this will strip out 146,250 to 219,375 ineligible disputes annually. Position your parsing tools to read those codes automatically, so eligibility determinations become a data step rather than a manual review. 

5. Plan for the IDR Gateway as a transition, not a cutover. Full platform functionality is anticipated within 24 months, with rolling guidance and feature launches beginning in Summer 2026. Treat this as a multi-phase migration. Assign an owner to track each guidance release, because several downstream deadlines – batching operational changes, registry applicability, open-negotiation reforms – are pegged to when the Departments announce specific portal functionality, not to a fixed calendar date. 

Where this gets difficult to do 

None of this is conceptually hard. The hard part is that your team is already at capacity, and this rule asks them to rebuild models, re-map inventory, and monitor a stream of rolling guidance, all at once, and mostly before the changes fully land. 

If you can only do one thing, do the threshold rebuild for your two highest-volume OON service lines. That single move captures most of the recoverable value, because the fee reduction hits high-volume, low-dollar claims hardest. Everything else, including full batching automation, CARC/RARC ingestion, Gateway migration, can follow in sequence once the economic case is proven on those first two lines.

The realistic risk isn't that you'll get the strategy wrong; it's that the guidance will roll out in pieces over 24 months, and a stretched team will miss a functionality announcement that starts a 90-day clock. Someone needs to own that calendar. 

Where EnableComp can help 

Resetting IDR threshold economics across every specialty and service code, and then keeping pace with rolling guidance for the next two years, is exactly the kind of complex-claims work that rewards scale and specialization.  

EnableComp models federal IDR ROI at the service-code level and manages the full dispute lifecycle, so your team captures the newly viable claims without absorbing the analytical and monitoring burden internally.  

If you want a service-line-by-service-line view of what the $15 fee and 50-item batching change for your specific denial inventory, let's build that model for your health system or hospital together.  Reach out today.


About the author 

Gordon Jaye, MPH, MScPM, is the Senior Vice President of Solution Engineering at EnableComp and a Six Sigma Black Belt. He brings extensive healthcare-operations leadership focused on optimizing patient access, patient satisfaction, and front-end revenue cycle efficiency. Gordon  specializes in strategies that improve patient flow, reduce wait times, and streamline intake through technology and process improvement. He is known for driving transformational change with rigorous financial oversight. 

CMS 2027 Payment Notice Final Rule: What it means for hospital revenue cycle teams

CMS final rule lowers costs, cracks down on fraud, and expands state control.

CMS is describing the 2027 Payment Notice as a win: lower user fees, less fraud, more state control. For a hospital system's revenue cycle, the same rule reads differently. Your patient access team is already spending more time chasing coverage status than it did a year ago; starting in 2027, that work gets harder while the coverage behind it gets thinner. 

On May 15, 2026, CMS finalized the 2027 Payment Notice, the annual rule that governs ACA Exchange plans (see the CMS fact sheet). The table below lists the nine provisions that matter most.  The remainder of this guide translates the ones that hit your revenue cycle hardest into actions you can take starting this quarter. 

9 Key provisions at a glance 

Provision 

Detail 

1. SEP eligibility verification  Reinstates pre-enrollment verification for at least 75% of new Special Enrollment Period sign-ups starting in 2027. Additional income documentation required for very low-income enrollees and those without corroborating tax data. 


2. APTC eligibility narrowed  Starting in 2027, premium tax credit eligibility limited to citizens and a limited set of lawful immigrants, excluding refugees, asylum recipients, and others with lawful status. Aligns with One Big Beautiful Bill Act (H.R. 1). 


3. Low-income  SEP ban continues  Ban on the low-income SEP for households at 150% FPL extends beyond 2026. 


4. Federal Exchange user fees   

Reduced to 1.9% for FFE and 1.5% for SBE-FPs, down from 2.5% and 2.0% in 2026. 


5. Plan design flexibility  Eliminates the requirement that federal-exchange issuers offer standardized plan options; removes the cap on non-standardized plans. New pathway for non-network plans to be certified as QHPs — as early as plan year 2027 for state-based exchanges, and no later than plan year 2028 for the federal exchange 


6. Catastrophic plan expansion  Allows issuers to offer catastrophic plans with terms up to 10 consecutive plan years. Expands hardship exemption eligibility for enrollment in catastrophic coverage. 


7. EHB restrictions  Prohibits issuers from including routine non-pediatric dental services as Essential Health Benefits. Beginning plan year 2028, states must defray the cost of state-mandated benefits in addition to EHB. 


8. Broker & marketing standards  Standardized broker eligibility application and consent form (effective 2028); codified list of banned marketing practices (cash inducements, false zero-premium claims, enrollment timeline misrepresentations). 


9. State authority expansion  Provisions allow states to strengthen oversight over Exchanges by tailoring certification reviews to local market conditions.

ACA Final Rule Executive Brief

The number that frames everything 

Marketplace enrollment already fell roughly 5% to 23.1 million in 2026 after enhanced premium tax credits expired at the end of 2025. KFF projects an additional loss of about 4.8 million enrollees as those subsidies fully phase out.  

That matters because the people who leave are often the healthy ones. The silver-plan share dropped from 57% to a record-low 43%, bronze jumped from 30% to 40%, and the average Marketplace deductible rose 37% – from roughly $2,800 to $3,800. (HFMA analysis) 

A sicker, higher-deductible risk pool means more patient financial responsibility landing on your balance sheet. The 2027 rule accelerates that trend rather than cushioning it. 

"Lower costs" are real, but not for your balance sheet 

CMS is correct in stating that the rule lowers some costs. As the table above shows, it cuts federal Exchange user fees to 1.9% for FFEs and 1.5% for SBE-FPs. Those savings flow to issuers and, in theory, to premiums. 

But lower premiums are not lower cost for healthcare providers. The savings sit with plans and enrollees. The provider absorbs the other side of the rule: higher deductibles, more coverage gaps, and more uninsured patients – costs that show up as bad debt and uncompensated care.  

Why the revenue cycle feels this before finance does 

The rule tightens the front door while thinning the coverage behind it. Both effects hit patient access – the point where coverage is verified – long before they appear in a quarterly payer-mix report. 

HCA Healthcare assumed 80–85% of patients losing exchange coverage would become uninsured; its data now shows the migration is closer to one-for-one. That revision pushed HCA's full-year exchange headwind to $1.0–$1.2 billion for 2026 and – nearly double the $600–$900 million it projected in April. 

Three mechanisms drive it. First, CMS reinstates pre-enrollment verification for at least 75% of new Special Enrollment Period sign-ups, so more patients arrive mid-verification. Second, premium tax credit eligibility narrows to citizens and a limited set of lawful immigrants, aligning with the One Big Beautiful Bill Act (H.R. 1). Third, the low-income SEP ban at 150% of the federal poverty level continues past 2026. 

Standard eligibility workflows assume coverage is either active or not. These provisions create a large middle band  pending, ineligible-for-subsidy, or newly uninsured  that most front-end scripts don't handle. 

5 Front-end actions to take now to protect margin under the new rule 

The nine provisions in the table above are the what; the five moves below are where your team spends its time. Each maps to one or more provisions, ordered by revenue cycle workload rather than by the rule's own sequence. 

  1. Re-script SEP eligibility checks for the 75% verification rule.

Assume any SEP enrollee could be mid-verification at the point of service. If coverage shows pending, route to a financial counselor before scheduling non-urgent care rather than assuming denial. Build a status code for "SEP pending" so these accounts don't silently age into bad debt. 

  1. Flag APTC-ineligible populations at registration.

The narrowed subsidy rules will push refugees, asylees, and other previously eligible patients toward full-price or no coverage. If a patient's status suggests APTC ineligibility, trigger a self-pay and charity-care screening early, not after the first claim is denied. 

  1. Prepare for catastrophic-plan financial responsibility. 

The rule lets issuers offer catastrophic plans with terms up to 10 consecutive years and expands hardship-exemption eligibility. Treat catastrophic enrollees like high-deductible patients: verify remaining deductible up front, and offer payment plans before service where policy allows. 

  1. Build a non-network QHP watchlist now - a 2027 issue in state-based exchange states.

Non-network plans may be certified as QHPs as early as plan year 2027 in states operating their own exchanges, and no later than plan year 2028 on the federal exchange. When that lands, out-of-network encounters expand materially. Start tagging any non-network product in your area today so your out-of-network dispute-resolution workflow isn't caught flat-footed. 

  1. Add state-level Exchange tracking to commercial strategy.

The rule restores greater authority to states over certification and oversight, so rules will diverge state by state. If you operate across states, assign someone to monitor each Exchange's local rules; one national assumption will no longer hold.

Prioritizing what to do first when your front end is already stretched 

For many providers, front-end staffing is already stretched, and eligibility data from Exchanges is often incomplete at the point of service. Layering five new workflows onto a lean patient access team is not realistic in a single quarter. 

Triage.  If you do only one thing, do move #1 – the SEP verification re-script – because it touches the largest volume of patients starting in 2027. Add moves #2 and #3 next quarter. Move #4 up if you operate in state-based exchange states, where non-network plans could appear as early as 2027; otherwise treat #4 and #5 as planning items and revisit them when rate filings clarify who's actually offering non-network plans. 

One development to build into your planning: The rule is already in active litigation  and courts have acted. A federal judge in Maryland has stayed eight provisions of the 2027 rule, a coalition of cities, counties, physicians, and small businesses filed suit on June 3, 2026, and on July 31 a group of 22 states filed a separate challenge in the Northern District of California. Several verification-related provisions may be enjoined for 2027 while surviving for 2028, because H.R. 1 codifies similar requirements statutorily. Plan for the rule as written, but reconcile your 2027 workflows against the current stay list before hard-coding anything 

One caveat worth watching: Parts of the rule face ongoing litigation that could shift implementation timelines on some provisions. Plan for the rule as written, but keep an eye on the docket before hard-coding anything for 2028.  

HowEnableComp can help 

The provisions above all point in one direction: more coverage ambiguity, more out-of-network encounters, and more complex claims landing on your team. That is exactly the specialized, hard-to-adjudicate volume EnableComp exists to resolve.  

If the non-network QHP pathway and shifting Marketplace mix are on your radar, let's talk about how EnableComp can absorb the complex-claims load before it hits your bad-debt numbers. 


About the author 

Gordon Jaye, MPH, MScPM, is the Senior Vice President of Solution Engineering at EnableComp and a Six Sigma Black Belt. He brings extensive healthcare-operations leadership focused on optimizing patient access, patient satisfaction, and front-end revenue cycle efficiency. Gordon specializes in strategies that improve patient flow, reduce wait times, and streamline intake through technology and process improvement. He is known for driving transformational change with rigorous financial oversight. 

_____

Frequently Asked Questions    

What is the CMS 2027 Payment Notice? 

The 2027 Payment Notice is CMS's annual rule governing ACA Exchange (Marketplace) plans, finalized on May 15, 2026. It covers plan design, verification requirements, subsidy eligibility, and Exchange oversight for the 2027 plan year, including provisions on Special Enrollment Period verification, premium tax credit eligibility, catastrophic plan terms, and state authority over Exchange certification. 

How does the 2027 rule change Special Enrollment Period (SEP) eligibility verification? 

Starting in 2027, CMS reinstates pre-enrollment verification for at least 75% of new SEP sign-ups, with additional income documentation required for very low-income enrollees and those without corroborating tax data. This means more patients arriving at point of service with coverage still pending verification, rather than a clear active/inactive status. 

Who is affected by the narrowed APTC eligibility rules? 

The 2027 rule limits premium tax credit (APTC) eligibility to citizens and a limited set of lawful immigrants, excluding refugees, asylum recipients, and others with lawful status who previously qualified. This aligns with the One Big Beautiful Bill Act (H.R. 1) and will push some previously subsidized patients toward full-price coverage or no coverage at all. 

What are non-network QHPs, and when do they take effect? 

The rule creates a new pathway for non-network health plans to be certified as Qualified Health Plans (QHPs). States running their own Exchanges can certify non-network QHPs as early as plan year 2027; the federal Exchange must do so no later than plan year 2028. For providers, this means a likely increase in out-of-network encounters once these plans reach the market. 

The FTE drain: Why your hardest claims cost more than they collect

Most conversations about revenue cycle performance focus on collections and cash uplift. Those numbers matter, but they only tell you half the story. The other half is what it costs you to assign your in-house revenue cycle team to cases they are ill-equipped to handle – the ones where regulations are constantly changing, rules can vary state to state, and the complexity is far beyond the skills most RCM staff possess.   

When your most capable staff spend their days on the most complex claims, you pay for it in slower cash flow, lower reimbursements, and staff burnout that puts you at risk of losing your best people. The American Hospital Association found that the average hospital assigns 59 full-time employees to regulatory compliance alone, and about a quarter of them are clinicians who would otherwise be caring for patients.  Pulling that much FTE effort into time-intensive, complex claims management instead of patient care just doesn't make sense." 

--> Where your people spend their time matters as much as what they collect. 


Standard workflows clear most of your claims –  a small share quietly consumes your team's valuable time 

Most health systems are built to process routine claims through standard EHR workflows. A smaller share, the complex claims and denials, falls outside that model. These claims often involve third-party liability, coordination of benefits across payers, or payer-specific documentation rules that standard EHR workflows were never built to handle. 

You can see it in how these claims get processed. According to the 2024 CAQH Index, claim submission is now 98 percent electronic, but prior authorization is only 35 percent electronic, and the documentation attachments complex claims require barely reach 32 percent.  

--> The hardest claims are exactly the ones that still have to be worked manually. 

In my experience, the small share accounts for around one-third of a revenue cycle team's time and resources. These claims increase denial rates, delay reimbursement, and divert trained staff from the high-volume commercial work where they add the most value. 


The hardest claims take the longest to pay, which stalls cash flow  

A standard medical claim often settles in about thirty days. A complex claim, like VA disability, takes around 70 days, and some even take months or years to close. That's your most experienced people tied up for weeks on a single claim, and reimbursement timelines extend far beyond those for non-complex claims. 

Your valuable people's time drains away, and cash flow slows to a trickle. The FTE drain doesn’t stop at claims. Complex clinical denials, including DRG downgrades, ED downgrades, medical necessity disputes and coordination-of-benefits issues, carry the same burden, along with the after-the-fact recovery work like zero-balance reviews and post-bill DRG validation 

Fighting these denials is expensive. Premier estimates the cost of contesting a single denied claim at $57.23 in 2023, up from $43.84 the year before. Labor drives roughly 90 percent of that expense. 

Overloaded specialists burn out, and then they leave 

Skilled revenue cycle staff are hard to find and harder to keep, and the people who can work a complex claim are among the scarcest of all. When you put your team on the most frustrating work day after day, you raise the odds they burn out and leave. 

Administrative load drives a big portion of that burnout. A 36-hospital time and motion study found that documentation was the single largest use of nurses' time, at 35.3% of their shift, ahead of both care coordination and medication tasks. It’s the same in the revenue cycle, where the hardest claims carry the heaviest manual load. 

As a result, retention suffers. In a 2025 Black Book survey of more than 9,000 nurses, 69 percent named documentation burden and poor system usability as major reasons they wanted to leave. Hospitals with high turnover were 3.5 times more likely to be running difficult or outdated systems.  

--> Every hour lost to work better suited to a complexity expert makes it harder to keep the people you can't easily replace. 


5 Signs the FTE drain is already hitting you 

  1. Your best people are on your most difficult-to-resolve claims. Your most experienced staff spend more time on complex claims than on the high-volume commercial work where they recover more, faster.  
  2. Complex claims sit for months. They routinely stall past 60 to 90 days before they move, tying up the specialists assigned to them the whole time.  
  3. Appeals stop after the first round. Your team gives up once the first attempt fails, and recoverable revenue gets written off by default.  
  4. No one owns the complex work. Complex claims aren't a defined function, so the work gets absorbed across the team as it comes in, with no clear accountability or processing strategy.  
  5. Turnover clusters on the hardest claims. The people working on your most difficult claims are the ones most likely to burn out and leave.  

If three or more sound familiar, the drain is already costing you, in cash and in capacity. Working harder on the same claims won't fix it. Start by measuring how much of your team's time complex work actually consumes, then decide which of it belongs in-house and which belongs with a complexity expert. 


The real lever is who works your complex claims 

You can't avoid these high-difficulty claims; they come with caring for patients, and the volume isn't going down. What you can decide is how the work gets done and who does it. 

That turns staffing for this claims segment into a strategic decision, one that directly affects your financial performance. Instead of spreading your team evenly across every claim type, put your people on the work where they recover the most, and bring in experts for the hardest cases. 

Example of how a complexity expert gets to root cause, not just the claim  

Consider a common case. A VA claim gets denied because an authorization never made it into the record. Your in-house associate can appeal and win the payment back, and most operations stop there. A complexity expert goes deeper, tracing that missing authorization back to registration, so the next VA claims don't fail the same way. 

--> By the time a claim is denied or underpaid, the money has already walked out the door, and preventing that loss costs far less than chasing it. 


Turning complexity into control 

Collections tell you what came in. They don't tell you what it cost to get there, or what your best people could have been doing instead.    

This is the problem EnableComp was built to solve. Its approach, Complex Revenue Intelligence, is designed to uncover hidden revenue, adapt to payer and policy changes, and help revenue cycle leaders act before revenue is lost. It runs on the  e360 RCM platform®, an AI-driven rules engine trained on one of the industry's largest complex revenue cycle datasets, more than 60 million processed claims, and it submits claims electronically about 10 times faster than the industry average. 

It brings more than 25 years of specialized expertise to the same three areas that drain your FTEs: complex claims like VA and workers' compensation, complex denials like DRG and ED downgrades, and revenue recovery like zero-balance review and DRG validation.  

Recovering even a fraction of that FTE drain means more revenue captured and less burnout among the people you can least afford to lose. 

The complex revenue cycle doesn't have to be a constant drain. Learn how EnableComp helps hospitals manage complex claims, denials, and revenue recovery. 


About the author

Zachary Schultz, CSMC, CRCR, is a nationally recognized expert in Veterans Affairs, Out-of-State Medicaid,  and Workers’ Compensation policy and claim reimbursement. As the VP of Solutions Engineering at EnableComp, he maintains relationships with state regulatory agencies, large PPO networks, and payers. He also monitors and analyzes legal developments and legislative changes that impact EnableComp’s business and healthcare partners. Before joining EnableComp, he spent 10 years in operational management roles and served in the US Army, with deployments to Afghanistan for Operation Enduring Freedom. 

What is a zero balance review? (And why your hospital is leaving money behind)

Your AR dashboard looks clean. Denials are trending down, follow-up queues are current, and thousands of accounts have closed at zero. That's the problem. 

A closed account and a correctly paid account are not the same thing. Some of what your team marked "resolved" was actually written off, adjusted in error, or paid by the wrong payer.  For many providers, once the balance hits zero, nothing in the workflow ever looks at it again. 

The problem is bigger than most finance teams assume  

Hospitals absorbed $130 billion in underpayments from Medicare and Medicaid in 2023 alone, and those shortfalls have grown roughly 14% a year since 2019, according to the American Hospital Association's Costs of Caring report. 

Commercial contracts add another layer on top: Industry benchmarking puts contractual underpayments as high as 7% to 11% of net patient revenue. None of that shows up as open AR. It shows up, if it shows up at all, buried inside accounts your system already considers finished. 

A zero balance review is a retrospective audit of closed accounts, built to find the revenue that never should have been written off. 

This post explains why zero balances hide errors, where those errors come from, and how to build a review process that gets the money back before your window to recover it closes. 

Why a $0 balance doesn't mean the claim was paid right 

Closing an account at zero only means the debits and credits net out to nothing in your billing system. It says nothing about whether the payer paid the contracted rate, billed the correct party, or processed the claim at all before it was written off. 

Primary failure patterns  

These failure patterns account for most of the recoverable revenue inside zero balance populations: 


primary failure patterns spotted in zero balance review audits


The flaws in standard AR workflows that result in revenue leakage 

Most revenue cycle teams are built to chase open balances, not closed ones. Follow-up queues, denial worklists, and AR aging reports all trigger off accounts that still show a dollar amount due. Once an account nets to zero, it drops out of every one of those workflows by design. 

That's not a staffing failure – it's how the systems are built. Nobody is assigned to re-open a resolved account and ask whether "the resolution" was correct. Meanwhile, timely filing limits and payer audit windows keep running, whether or not anyone is looking. The longer a zero balance error sits, the narrower the path to recovering it gets. 

Where to start: A five-part review process 

A structured zero balance review turns an invisible problem into a working queue, the same way denial management does for open claims. Five actions make up the core of that process: 

  1. Run periodic retrospective reviews of closed accounts, prioritized by payer, claim type, and dollar threshold. Don't try to review everything – start with the payers and claim types most likely to carry contractual complexity or high dollar volume. 
  2. Build or contract for detection logic that flags anomalies automatically. Two rules do most of the work: adjustment amounts that exceed expected contractual variance, and write-off codes that don't correspond to any documented denial or appeal. 
  3. Fix coordination of benefits upstream, not downstream. Verify payer sequencing and eligibility at registration, not at billing. Every COB error caught before the claim goes out is one that never becomes a zero balance problem later. 
  4. Attach every finding to a timely filing checkpoint. An identified underpayment is only recoverable if it's worked before the payer's reconsideration window closes. Build the deadline into the workflow, not just the finding. 
  5. Feed findings back into contract management. If one payer shows a repeated pattern of underpayment, that's not a one-off recovery – it's a compliance issue that belongs in your next renegotiation. 

If a payer or claim type shows systematic underpayment across multiple accounts, escalate it to contracting immediately rather than waiting for the next full review cycle. 

Five Part Zero Balance Review Process

The honest obstacle: Most teams don't have the bandwidth 

Here's what makes this hard to act on: your team is already stretched thin managing open AR and current denials. Zero balance review is additive work that requires access to historical claims and remit data that isn't always easy to pull.  It also competes for attention with problems that are more visible day to day. 

If you can't stand up a full review program right now, triage. Start with a single high-dollar payer or claim type – workers' compout-of-network Medicaid, or another category with known contract complexity – and run one retrospective pass before expanding. A narrow, consistent review beats a comprehensive one that never gets off the ground. 

How EnableComp can help  

EnableComp's zero balance review process applies specialized analytics along with clinical and billing expertise to find recoverable revenue in closed accounts that standard AR workflows miss.  

Instead of a manual audit, EnableComp uses systematic detection logic to surface underpayments, erroneous write-offs, and COB errors at scale, paired with a recovery workflow built around payer-specific timely filing requirements. If a triage pass on your highest-dollar payer surfaces the patterns described above, that's the signal it's time for a structured review. 

Schedule a consultation to see how much revenue you’re leaving behind. 


About the author 

Kelsey Taylor, BSN, RN, is the Senior Director of Clinical Denials at EnableComp, bringing over 10 years of experience in healthcare management and clinical operations to the role. Her background spans clinical quality, care management, and product management, giving her a well-rounded lens on how revenue cycle, training, and clinical operations intersect. She's passionate about empowering teams to deliver patient-centered, impactful results and frequently speaks on topics like DRG revenue integrity, complex revenue recovery, and denial prevention strategy. 


How to appeal a DRG downgrade: A step-by-step guide

Payer denials are not new to revenue cycle leaders. But DRG downgrades represent a particular kind of threat: one that often arrives quietly, weeks after discharge, buried in a post-payment adjustment. By the time your team catches the downgrade, the revenue has already walked out the door. 

This guide walks through the DRG downgrade appeal process from triage to escalation, with a focus on what truly moves the needle for revenue cycle teams. You will learn how to identify the highest-risk DRGs, build a defensible appeal, and put the right people on the right denial type. More importantly, you will learn how to stop treating appeals as one-off firefighting and start running them as a systematic revenue recovery function. 

The numbers tell a stark story 

According to the American Hospital Association, Medicare Advantage claim denials increased 55.7% between 2022 and 2023, while commercial denials rose 20.2% over the same period.  

Hospitals spent nearly $18 billion in 2025 alone fighting to recover payments they had already earned. For a revenue cycle operation running on thin margins, that is not sustainable. 

The good news is that this is a winnable fight. A 2024 Premier Inc. analysis found that more than 54% of denied claims are ultimately overturned. The hospitals recovering revenue share one thing in common: A systematic approach to appeals.  

Why DRG downgrades are different 

An outright denial is visible. A DRG downgrade is not. Payers conduct retrospective reviews and reassign a lower-weighted DRG, often weeks or months after the claim was paid. The result is a quiet, compounding revenue drain that can be easy to miss in a high-volume environment. 

The downstream consequences extend beyond individual claims. Repeated downgrades suppress your Case Mix Index (CMI), signaling to payers and regulators that your hospital serves a less complex patient population. A lower CMI reduces prospective payment rates, weakens your negotiating position with commercial payers, and can invite additional scrutiny. One downgrade is a billing dispute; a pattern of downgrades is a strategic liability. 

Medicare Advantage plans have been the most aggressive in pursuing these adjustments. What many hospitals do not fully leverage is that CMS rules require MA plans to follow standard Medicare coding policies and ICD-10 guidelines. That is not just regulatory background; it is a direct line of defense in your appeal. The threat has grown more sophisticated in recent years. 

Payers using AI to downgrade DRGs at scale: A growing threat 

Payers are increasingly deploying automated algorithms and AI-driven audit tools to flag and downgrade DRGs at scale, often before any human clinical reviewer touches the claim. 

The AHA has specifically identified machine learning algorithms as a driver of denial growth, noting that poor applications of these tools result in automatic denials without consideration of a patient's individual clinical circumstances or review from a clinician or plan medical director.  

For revenue cycle teams, this changes the nature of the appeal. When a denial originates from an algorithm rather than a physician reviewer, the response strategy is different. You are not rebutting a clinical judgment; you are challenging an automated decision that may have applied rigid criteria without accounting for the full complexity of the case. That distinction matters when building your appeal, selecting your escalation path, and deciding when to request a peer-to-peer review. 

Know where you are most vulnerable 

Payers do not audit randomly, but rather they concentrate reviews on high-weight DRGs where a downgrade yields the largest financial return. Understanding which cases carry the most exposure is the first step toward protecting rightful revenue reimbursement. 

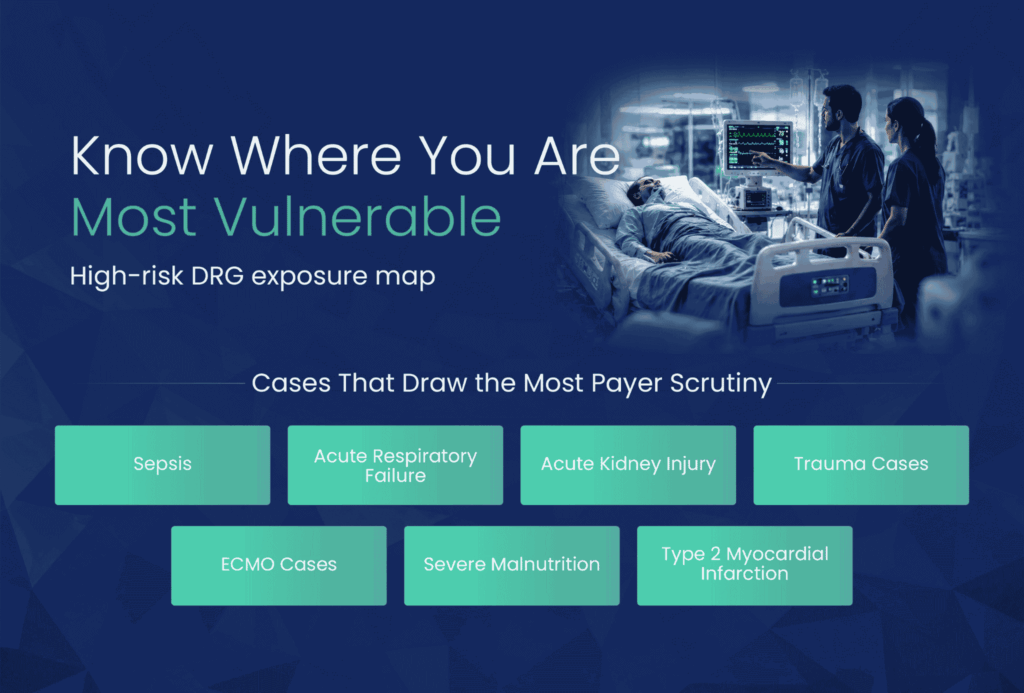
The diagnoses that consistently draw the most scrutiny include sepsis, acute respiratory failure, acute kidney injury, severe malnutrition, and type 2 myocardial infarction.  

Type 2 MI is frequently targeted because demand ischemia is often documented as a secondary finding rather than the principal diagnosis, and payers require specific documentation linking the underlying cause to the MI designation. Severe malnutrition denials turn on whether the record explicitly supports the criteria for that severity level, including the specific indicators the clinician used to arrive at that diagnosis, such as weight loss, reduced intake, or functional decline. 

In both cases, a concurrent CDI query during the encounter is far more effective than a post-discharge appeal. Trauma cases and patients requiring ECMO are also high-risk, given the complexity of documentation those cases demand. These are not obscure edge cases; they are common high-acuity admissions that appear in nearly every inpatient facility.

DRG Downgrade review - know where you're most vulnerable

The financial stakes per case are significant 

Overturning a sepsis downgrade can recover between $3,000 and $7,000 per claim. Multiply that across volume, and the revenue impact becomes clear. 

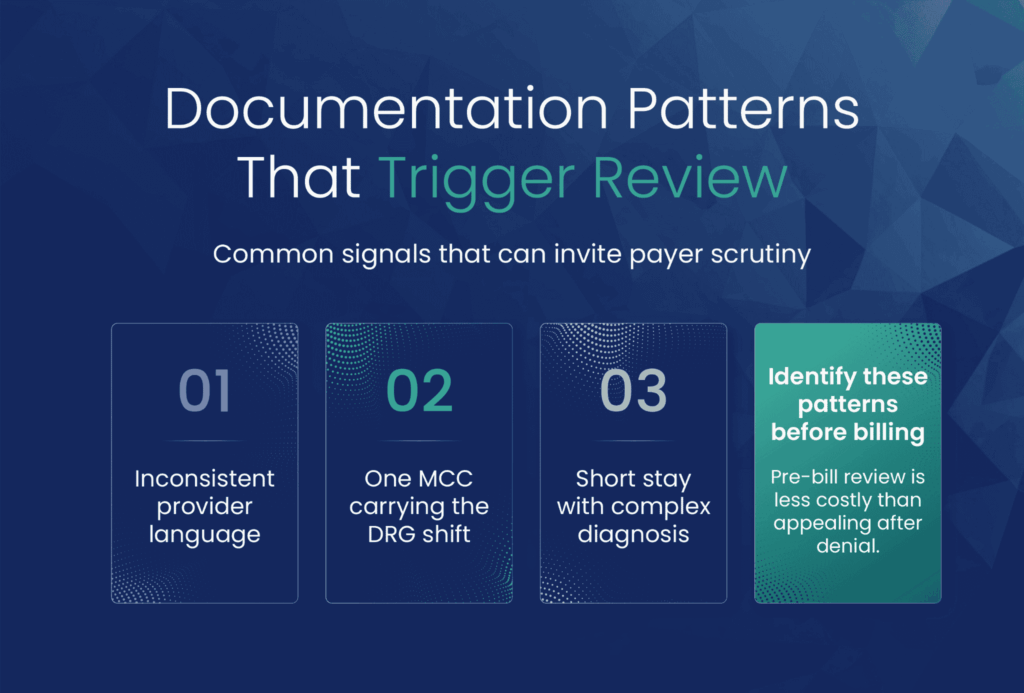
Certain documentation patterns invite denials even when the clinical picture is straightforward. Inconsistent language across providers, a single MCC carrying the entire DRG shift, and a short length of stay paired with a complex diagnosis are all triggers that flag cases for payer review. Identifying these patterns before billing is far less expensive than appealing them after.

DRG downgrade appeal - documentation patterns that trigger review

The distinction that determines your strategy 

Before building an appeal, your team needs to answer one question: What kind of downgrade is this? 

There are two distinct types, and they require fundamentally different responses. Getting this wrong is one of the most common and costly mistakes in the appeals process. 

The first is a coding-based downgrade. The payer disputes the ICD-10 code assignment itself: the sequencing of diagnoses, the selection of a CC or MCC, or the application of coding guidelines. These appeals are built on ICD-10-CM Official Guidelines, AHA Coding Clinic references, and UHDDS definitions. A strong coder and CDI specialist can lead this defense. 

The second is a clinical validation denial. Here, the payer is not challenging the coding; it is challenging whether the clinical evidence in the record supports the diagnosis at all. A common example is sepsis: A case documented under Sepsis-2 criteria may be denied by a payer applying the narrower Sepsis-3 standard. 

 ICD-10-CM Official Guidelines and AHA Coding Clinic do not require Sepsis-3 criteria for diagnosis coding, meaning a payer applying a Sepsis-3 threshold is imposing a standard that exceeds CMS coding guidance and is a contestable overreach, not a legitimate basis for denial. 

This type of denial requires a physician advisor to lead the response, with a clinical narrative that addresses the acuity of the case in medical terms. 

Some denials combine both elements. Recognizing that early allows you to mobilize the right resources without losing time.  

The appeal process, step by step 

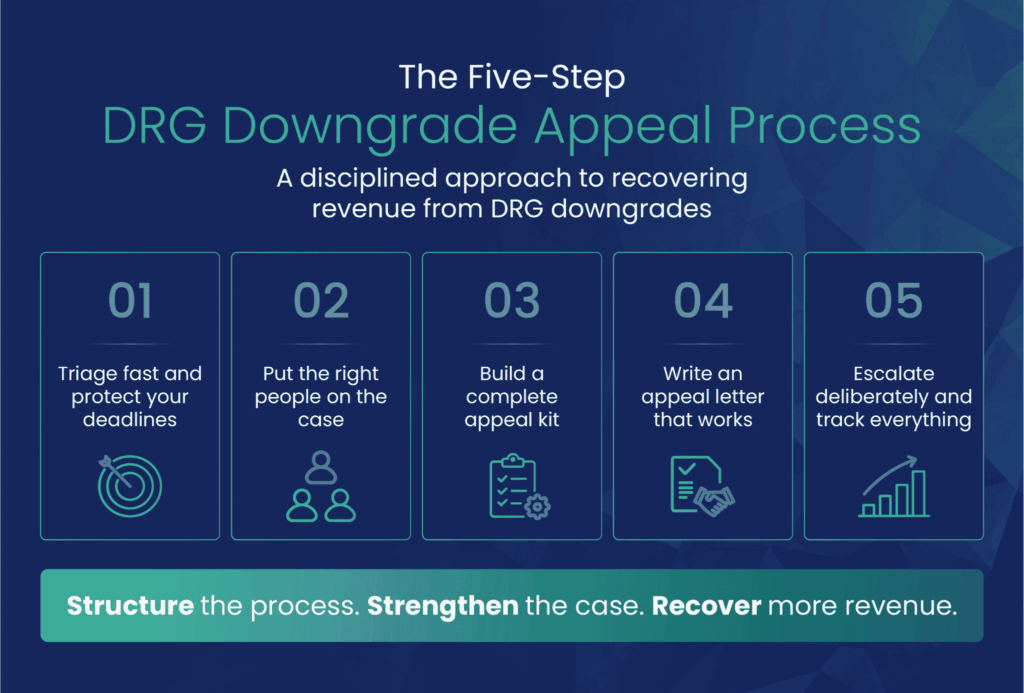
DRG downgrade appeal - five-step drg downgrade appeal process

Step 1: Triage fast and protect your deadlines 

The moment a downgrade is identified, the clock is running. Appeal windows vary widely by payer, from 30 days to one year, and a missed deadline forfeits your right to dispute entirely. Deadline management is not an administrative detail; it is a revenue protection function. 

For Medicare fee-for-service, the process follows a five-level path:  

  1. MAC redetermination  
  2. QIC reconsideration  
  3. ALJ hearing   
  4. Medicare Appeals Council review  
  5. Federal court 

Medicare Advantage plans are required to provide the same five-level structure under CMS rules. For commercial payers, appeal rights are contract-specific, so reviewing the payer agreement and the explanation of benefits language is an essential first step. 

Your triage process should identify the downgrade type, assign the right team, and confirm the deadline before anything else moves forward. 

Step 2: Put the right people on the case 

The appeal team should match the denial type. For a coding-based downgrade, that means your lead coder and CDI specialist. For a clinical validation denial, a physician advisor is not optional; it is the foundation of the appeal. Payer medical directors respond to peer-level clinical arguments in ways they simply do not respond to coding citations alone. 

Before launching a formal written appeal, consider requesting a peer-to-peer review with the payer's medical director. This step alone resolves a meaningful share of clinical validation disputes and avoids the time and cost of a full written escalation. A revenue cycle lead should own the process end-to-end: tracking deadlines, coordinating team members, and managing escalation timing. 

Step 3: Build a complete appeal kit 

One of the most consistent findings in DRG downgrade cases is that payers issue denials without having thoroughly reviewed the medical record. Do not assume they have read it. Submit the complete record with your appeal and make the relevant clinical evidence impossible to overlook. 

Start with a clinical timeline: from the patient's ED presentation through labs, imaging, treatment decisions, and clinical course. Then layer in the objective markers specific to the diagnosis in question.  

Pair the clinical evidence with authoritative coding references: The ICD-10-CM Official Guidelines from CMS and relevant AHA Coding Clinic guidance. Then pull the payer's own medical policy and identify precisely where the record meets their stated criteria. Finally, annotate the denial letter directly, addressing each stated rationale with a specific, documented rebuttal. 

Step 4: Write an appeal letter that works 

The appeal letter is where the case is won or lost. Structure matters as much as content. 

Open with the regulatory grounding: the applicable ICD-10-CM coding guidelines, UHDDS principal diagnosis definitions, and, for MA plans, the CMS requirement to follow standard Medicare coding rules. Establishing the governing framework early tells the reviewer this appeal is built on policy, not preference. 

Then tell the clinical story. Narrate the acuity of the case: what the patient presented with, how the clinical picture evolved, what treatment decisions were made and why. A list of diagnosis codes does not convey complexity. A well-constructed clinical narrative does. 

Address the payer's denial rationale directly and specifically. Ignoring their argument signals weakness; dismantling it signals command of the case.  

For clinical validation denials, lead with the physician advisor's attestation and let the clinical evidence carry the argument. Throughout, keep the tone professional and factual. Adversarial language rarely helps and can invite dismissal at the first level of review. 

Step 5: Escalate deliberately and track everything 

Most hospitals stop appealing after the first denial. That is exactly what payers count on. The data supports persistence: Over 54% of denied claims are eventually overturned, with commercial payers reversing more than 60% of initial denials. The revenue is there to be recovered. 

Know your escalation path and the timing requirements at each level before you need them. ALJ hearings and external reviews are not last resorts; they are legitimate tools that frequently produce favorable outcomes for well-documented cases. 

Treat every payer interaction as part of the record: Log dates, contacts, responses, and outcomes. Over time, this data becomes your pattern file, revealing which payers are systemically downgrading specific DRGs and building the case for a broader response. 

Note: Under CMS-4208-F, which was made effective January 1, 2026, once an MA plan approves an inpatient admission, it generally cannot reverse that approval based on information gathered after the fact. Plans may normally reopen only for fraud or obvious error. Hospitals that are not aware of this protection may be conceding mid-stay reversals they no longer have to accept.  

Shifting from reactive to proactive 

Winning appeals is important; not needing to appeal is even better. 

The most effective strategy is pre-bill clinical validation review for every high-risk DRG before the claim goes out. CDI involvement should be concurrent, not retrospective; documentation gaps are far easier to close during the encounter than after discharge.  

Engaging physicians directly, and showing them specifically how their documentation affects reimbursement and audit exposure, is one of the most effective CDI tactics available. 

CMS updates DRG logic, CC/MCC designations, and documentation requirements every fiscal year through the IPPS final rule. Annual training for coding and CDI staff on those updates is not optional if you want to avoid preventable denials.  

The PEPPER report, a free CMS benchmarking tool, allows hospitals to compare DRG coding patterns against national norms; coding within normal ranges is both a compliance indicator and a defense against payer scrutiny. 

Track denial trends monthly by payer, DRG, and diagnosis. A pattern of downgrades on a specific DRG from a specific payer is not a coincidence; it is a signal of systemic audit activity, and for public payers, it can precede recoupment extrapolation across a broader population of claims. Getting ahead of that pattern is less expensive than responding to it. 

Building appeal kit templates for your highest-risk DRGs removes the friction from the process. When a denial arrives, your team should not be starting from scratch; they should be activating a documented workflow. 

The bottom line 

DRG downgrades are not inevitable losses. They are recoverable revenue, and the hospitals capturing that revenue are the ones that treat appeals as a systematic revenue protection function rather than a case-by-case administrative burden. 

Every uncontested downgrade is a permanent write-off. Every pattern left untracked is a compliance risk. And every dollar recovered through a successful appeal is proof that the investment in a disciplined DRG audit process returns far more than it costs. 

DRG downgrade appeal - is your current drg review process strong enough

About the author 

Kelsey Taylor, BSN, RN, is the Senior Director of Clinical Denials at EnableComp, bringing over 10 years of experience in healthcare management and clinical operations to the role. Her background spans clinical quality, care management, and product management, giving her a well-rounded lens on how revenue cycle, training, and clinical operations intersect. She's passionate about empowering teams to deliver patient-centered, impactful results and frequently speaks on topics like DRG revenue integrity, complex revenue recovery, and denial prevention strategy. 

The cost of claim denials: Hospital revenue leakage statistics CFOs should know

You don't need to be convinced that denials are a problem. You're living it.

In a recent survey of hospital and health system executives, nearly 81% reported that rising denial rates are a major stressor. The frustration is real, and so is the revenue walking out the door. 

What makes the problem more difficult is that most providers don't have a clear view of what denials are actually costing them. Blended metrics that lump routine administrative denials together with complex clinical disputes can make overall performance look stronger than it is, while significant revenue leakage goes undetected. 

Then there's the cost of fighting back. Appealing a denial isn't free, and for high-volume environments, the math on whether to pursue a claim isn't always straightforward. Meanwhile, payers are getting faster and more sophisticated, and most hospitals are not keeping pace. 

This article cuts through the noise with the denial statistics every CFO should have on their radar: where revenue is slipping through the cracks, why the full scope of the problem is so difficult to see, and what leading health systems are doing differently to get ahead of it. 

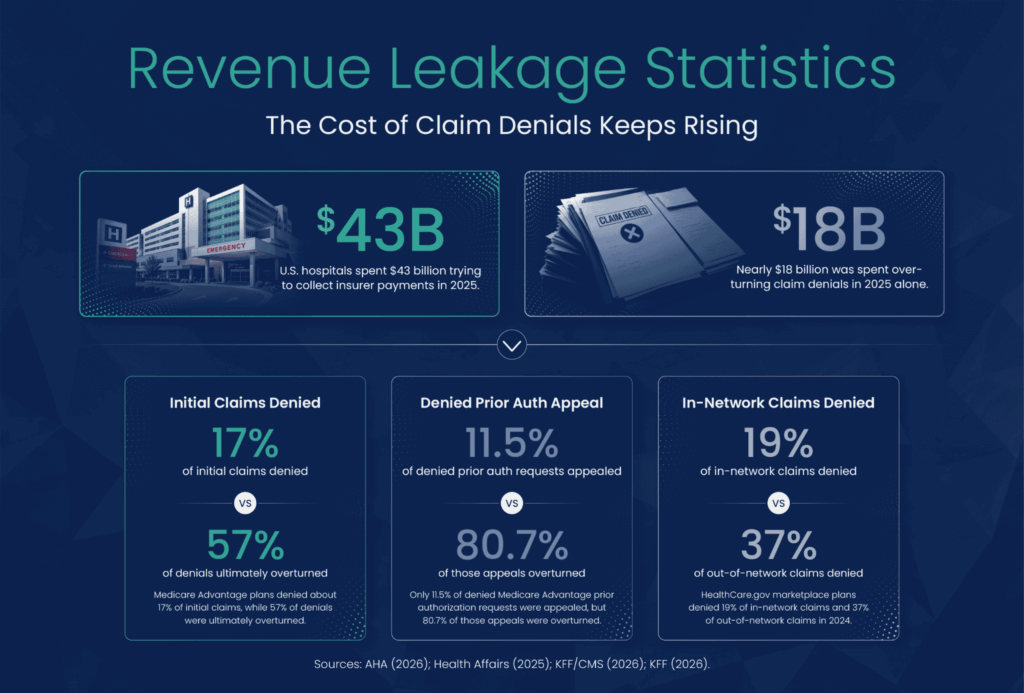
Revenue Leakage Stats - cost of claim denials

Denial rates are rising across every payer type 

Denial pressure is broad-based, with strong independent signals from Medicare Advantage and the ACA marketplace. Health Affairs analysis found that Medicare Advantage plans denied approximately 17% of initial claims, with 57% ultimately overturned. 

KFF's analysis of CMS transparency data found that HealthCare.gov marketplace plans denied 19% of in-network claims and 37% of out-of-network claims in 2024. The same report found that administrative reasons accounted for 25% of in-network denial reasons, reinforcing the need to separate preventable denials from more complex payer disputes. 

For hospital finance leaders, rising denial rates are not only an operational problem; the dollars behind those denials are a cash problem. When those dollars remain unresolved or fall out of appeal workflows, the result is revenue leakage. 

Blended metrics can hide revenue leakage 

High-level denial reporting has value, but it can mask leakage.   

While the cost of processing a routine claim is typically around $7 to $10 across payers and providers, EnableComp, which specializes in RCM complexity, estimates costs for processing a complex claim can be three to ten times that, with some claims costing even more. That spread matters because complex denials often require clinical review, coding expertise, regulatory knowledge, and payer-specific escalation. 

When standard and complex denials are grouped, high-volume administrative recoveries can make performance look strong, while a smaller set of complex cases creates disproportionate exposure. 

The price hospitals pay just to recover what they're owed 

In 2025, U.S. hospitals spent $43 billion trying to collect payments from insurers for care already delivered.  

The average cost to rework a denied claim is between $25 and $181. Overturning claims denials costs hospitals nearly $18 billion in 2025 alone.  

For high-volume denial environments, those rework costs compound quickly, leaving revenue cycle teams to weigh whether each claim is worth pursuing. It's a calculation that doesn't always get made accurately or at the right scale. 

Recoverable denial revenue is slipping through the cracks 

Only 11.5% of denied Medicare Advantage prior authorization requests were appealed, and of those, 80.7% were overturned. The appeal process works, but resource constraints and ROI concerns quietly push recoverable revenue off the table before the fight even starts. 

For hospitals operating under margin pressure, unworked denials become write-offs. Complex cases routed into standard queues can age past the point of recovery, and reimbursement for delivered care provided never arrives. 

Silent denials 

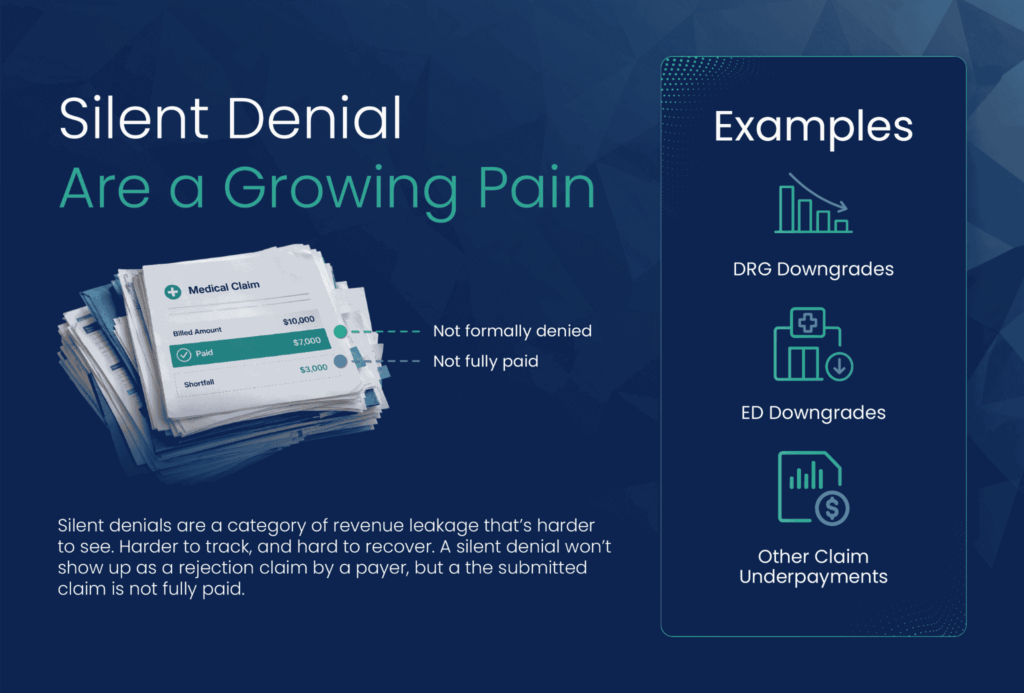
Not every revenue loss shows up as a denial. A silent denial won’t show up as a rejected claim by a payer, but the submitted claim is not fully paid either. 

DRG downgrades, Emergency Department (ED) level-of-care downgrades, and other underpayments arrive as payment reductions rather than formal denial notices, which means they often bypass the workflows built to catch them. For many hospitals, these losses are hidden in plain sight. 

DRG downgrades alone can represent significant dollars per claim. When a payer recodes a case to a lower-weighted diagnosis, the revenue difference rarely triggers the same urgency as an outright denial, even when the financial impact is comparable or greater. The same is true for ED downgrades, where payers reduce the level of care billed without issuing a formal denial that revenue cycle teams would typically flag and pursue. 

Silent denials are a category of revenue leakage that's harder to see, harder to track, and harder to recover. Many hospitals aren't measuring it at all, not because they're not paying attention, but because their denial management systems weren't built to surface it. If your team is only tracking what's formally denied, you're likely underestimating your total exposure by a meaningful margin. 

silent denials

Payers are getting faster and more sophisticated at claim review 

Payers are using AI and advanced analytics to review claims across broader datasets and at faster speeds. A Stanford-led review  evaluated 21 AI tools active across utilization review and described the dynamic as an "arms race." An NAIC survey of 93 large health insurers found that 84% were already using AI in their operations. 

The question for providers is not whether to match payer AI with provider AI. Most organizations will not win an arms race based on technology alone. The more practical challenge is to understand how payer behavior is changing and direct expertise toward the claims that carry the greatest financial risk. 

The pressure is not always where hospitals expect. Hospitals can strengthen the mid-cycle with better documentation, analytics, and earlier intervention. But technology alone will not close the gap.  

Complex denials involving payer-specific audit patterns, post-payment adjustments, and clinical validation still require experienced review and clear escalation paths. For many organizations, working with RCM experts focused on complex denial categories is becoming a practical revenue-protection strategy.  

The next generation of denial management 

The next generation of denial management is less about adding another appeal queue and more about building revenue intelligence around claims already in motion. 

Leading organizations are treating denial management as more than a back-end collections process. The goal is not only to overturn more denials faster but also to understand which revenue is most at risk, where denial patterns are emerging, and where earlier intervention can prevent future write-offs. 

That shift matters because treating every denial with the same level of effort is not a strategy. The advantage comes from better prioritization, earlier intervention, and the ability to learn from denial patterns over time.   

What providers can do about denial-related revenue leakage 

When denial rates climb, the answer is not simply to work faster. The stronger strategy is to segment denials by complexity, recoverability, and financial risk.  Here’s where to start: 

Strengthen front-end processes to prevent avoidable denials 

Registration, data verification, and prior authorization errors remain common causes of claim denials. Real-time eligibility checks, cleaner intake workflows, stronger authorization tracking, and better documentation practices can prevent many routine denials before they reach the payer. 

Segment denial performance by complexity and financial exposure 

Separating standard denials from complex clinical and payer-specific denials lets revenue cycle teams track each category by dollar value, recovery rate, time to resolution, and aging. Specialized resources should be directed toward the claims with the highest financial risk and strongest likelihood of recovery. 

Invest in the right people and vendors  

Denial management depends on coordination among patient access, clinical documentation, coding, case management, finance, and payer teams. Complex denials often require clinical judgment, coding expertise, and payer-specific knowledge, making cross-functional accountability essential.  

Use technology to move from reactive to predictive  

Technology should help teams see patterns earlier, not just move denied claims through a queue faster. Hospitals need to understand which payers are changing behavior, which categories are growing, which service lines are most exposed, and which claims are most likely to recover before write-offs accumulate. 

The goal is to move from chase-and-collect to predict-and-prevent. 

The revenue you recover depends on the work behind the denial 

Denial rates are rising. Rework costs are increasing. Recovery is taking longer. Payers are also becoming more sophisticated in how they review, downgrade, and challenge claims. The hardest dollars to recover are often tied to complex clinical and payer-specific denials that standard workflows were not designed to resolve. 

That is the real cost of claim denials: delayed cash, avoidable rework, premature write-offs, and complex cases that never receive the right review. 

The organizations that perform best will not necessarily be those with the lowest denial rates alone; they will be the ones with the visibility, expertise, and processes to respond before recoverable revenue is lost.  

How EnableComp can help 

Most denial management approaches treat all denials the same, and that's exactly where revenue gets left behind. EnableComp specializes in the complex denials that are hardest to see, hardest to fight, and most likely to be abandoned before recovery. That means DRG downgrades, ED downgrades, underpayments, and high-value clinical disputes that require specialized expertise and payer intelligence that most internal teams simply don't have the bandwidth to build. 

The hospitals seeing the strongest recovery results aren't working harder; they're working on the right claims with the right resources. If your organization is ready to understand where your true denial exposure lies and how much of it is actually recoverable, that's exactly the conversation EnableComp wants to have with you. Contact us now.  

EnableComp's Complex Denials Suite can help you

About the author 

Kelsey Taylor, BSN, RN, is the Senior Director of Clinical Denials at EnableComp, bringing over 10 years of experience in healthcare management and clinical operations to the role. Her background spans clinical quality, care management, and product management, giving her a well-rounded lens on how revenue cycle, training, and clinical operations intersect. She's passionate about empowering teams to deliver patient-centered, impactful results and frequently speaks on topics like DRG revenue integrity, complex revenue recovery, and denial prevention strategy. 

Medicaid work requirements are live

What hospital revenue cycle leaders must do before August 2026

Nebraska moved eight months ahead of the federal deadline. By January 2027, every expansion state must follow. 

On May 1, 2026, Nebraska became the first state in the nation to enforce Medicaid work requirements, launching eight months ahead of the federal deadline under H.R. 1 – the One Big Beautiful Bill Act.

By January 1, 2027, all 42 Medicaid expansion states and the District of Columbia must follow. That means every state in your Out-of-State (OSS) Medicaid patient portfolio will be affected within the next eight months.

The National Urban Institute estimates 4.9 and 10.1 million people will lose Medicaid coverage in 2028 due to work requirements and more frequent eligibility checks.

Revenue cycle leaders must plan for disruption

For revenue cycle leaders, the question is not whether this will create claim disruption: It will. The question is whether your organization will be positioned to manage the surge in eligibility volatility and OOS Medicaid denials – or be caught flat-footed when the first wave hits in August 2026.

How we got here

Nebraska's path is the product of three forces: a voter mandate, a federal law, and a state choice to accelerate.

In 2018, Nebraska voters approved Medicaid expansion by ballot initiative. Coverage extended to adults up to 138% of the federal poverty level.

In July 2025, H.R. 1 (the One Big Beautiful Bill Act, or OBBBA) was signed into federal law. It required all 42 expansion states and DC to implement community engagement requirements by January 1, 2027.

In December 2025, CMS approved Nebraska to launch eight months ahead of the federal deadline, effective May 1, 2026.  The requirements apply to new applicants as of May 1st and existing enrollees will be assessed at first renewal on or after July 31, 2026.

The Urban Institute projects that 16,000 to 30,000 Nebraskans will lose coverage by 2028 out of the roughly 70,000–72,000 subject to the requirement. Many will lose coverage not because they are ineligible, but due to administrative failures such as missed paperwork, enrollment system friction, and lack of awareness.

The requirement applies only to the expansion population.

Qualifying activities

Who is exempt

Temporary hardships can also apply. These include hospitalization, residence in a federal emergency declaration county, or residence in a high-unemployment county.

The state estimates it can auto-verify 60% to 70% of affected members using existing data. The remaining 30% to 40%, roughly 21,000 to 28,000 people, must submit verification or declaration forms. Non-compliant members get 30 days to respond before disenrollment.

The August 2026 inflection point

The first material disenrollment activity in Nebraska will hit the cohort whose annual renewal periods end July 31, 2026. This means:

Where the financial pressure hits

For hospitals and health systems, the financial exposure operates on these timelines:

Immediate: Now through July 2026

The first phased renewal cohort, with end dates of July 31, 2026, will start showing up in claim data in August. Self-pay conversion and denial rates will drift before most teams have a clean baseline.

Phased rollout: August 2026 through June 2027

As existing enrollees cycle through their renewal months, eligibility losses spread across the year. That makes the trend harder to spot in any single month's denial report. Cohort-level segmentation is the only way to see it clearly.

National: By January 2027

Every expansion state in your patient mix becomes a source of disenrollment risk. Montana goes live in July 2026 and Iowa follows in December. The remaining 39 expansion states must launch by January 1, 2027.


Financial exposure for providers

The Nebraska Hospital Association reports that roughly 30% of Nebraska hospitals already operate without a sustainable margin. Bluestem Health, a Lincoln FQHC, has modeled $400,000 to $600,000 in additional annual losses. These are not abstract projections; they are direct hits to uncompensated care, charity volumes, and bad debt.

Not all providers will feel this equally. Beyond those impacted in Nebraska, the institutions most at risk in the near future are those with OOS Medicaid volume concentrated in states adjacent to early-adopter states.

Nebraska’s six bordering states – Iowa, Kansas, Missouri, Wyoming, Colorado, and South Dakota – represent the near-term exposure concentration. Hospital partners in these states that draw patients from Nebraska for trauma care, tertiary referrals, or specialized services will encounter the first wave of coverage disruption.

Structurally, the highest-risk providers share a common profile:

Critical access hospitals in border counties where patients routinely cross state lines for care.

As the January 2027 national deadline approaches, this exposure will broaden to every health system with any OOS Medicaid volume.

The doubled redetermination problem

Work requirement disenrollment is the most visible risk, but it is not the only one.

H.R. 1 mandates six-month redeterminations for the Medicaid expansion population – down from the typical 12-month cycle. This change doubles the frequency at which eligibility status can change for any given patient. For revenue cycle teams managing OOS claims, this means:

Operational impacts to providers

Work requirements shift much of the operational burden onto providers. When enrollees churn off coverage, even briefly, hospitals and clinics absorb the verification work, the care gaps, and frequently the unpaid bills. These four pressure points stand out:

1. Emergency department exposure

Many enrollees first present at the ED, and weeks-long enrollment windows leave hospitals absorbing costs when coverage lapses between visits.

2. Patient navigation burden

Many providers will absorb the front-end work of explaining requirements, documenting exemptions, and assisting with iServe submissions. NHA estimates 30%–40% of the 70,000 affected enrollees will need manual hour verification.

3. Continuity-of-care disruption

Coverage churn creates gaps in chronic disease management (diabetes, behavioral health, HIV, hemophilia) and care-plan execution.

4. Rural capacity strain

The Nebraska Rural Health Association notes already-understaffed rural hospitals would face the largest relative volume of disenrolled patients.

Actions revenue cycle leaders should take now

Revenue cycle leaders should be taking the following actions now, before the August 2026 denial wave begins.

Audit your OOS Medicaid exposure by state

Identify what share of your OOS Medicaid volume comes from Nebraska, Montana, Iowa, and the states adjacent to them. Quantify the AR exposure. This is your baseline for measuring impact and prioritizing response right now.

Stress-test your time-of-service eligibility processes

The primary failure point in work requirement environments is coverage that was active at the time of service but lapsed before billing. Front-end eligibility checks need to account for the six-month redetermination cadence and flag patients in OOS expansion states as elevated-volatility accounts.

Verify OOS provider enrollment is current in affected states

Work requirement disenrollment creates a secondary enrollment problem: Patients who lose and then regain coverage may do so under a different Medicaid managed care plan or fee-for-service pathway. Ensuring your organization maintains current provider enrollment across all OOS Medicaid programs is foundational to collecting on this volume.

Build denial response workflows now, not after August

OOS Medicaid denials for coverage loss require a different response than standard billing denials. Teams need clear protocols for retroactive coverage investigation, coordination of benefits review, and self-pay conversion workflows for patients who are permanently disenrolled.

Other impacts to anticipate

Beyond the clinical disruption, work requirements reshape the financial mechanics of serving the expansion population. Three areas warrant early attention:

  1. Self-pay and bad debt growth following coverage loss, particularly during the July 2026–June 2027 phased renewal window.
  2. Higher charity care and counseling demand. Expect added FTE pressure on patient access and financial counseling teams.
  3. Mid-AR coverage status changes will become significantly more common.

How EnableComp can help

As Medicaid eligibility becomes more volatile under H.R. 1, the revenue at greatest risk isn't always where hospitals are looking. OOS Medicaid claims – already among the most complex to enroll, bill, and collect on – get harder still when patients are cycling on and off coverage in their home states.

EnableComp’s signature Complex Revenue Intelligence™ approach and e360 RCM® platform are purpose-built to recover dollars many organizations write off.

For hospitals and health systems preparing for the August 2026 redetermination window and the January 2027 federal deadline, here a few areas where we can help right now:

The August window is three months away. Let's start with your OOS Medicaid exposure today. Talk to an EnableComp Expert (link).

About the Author. Gordon Jaye, MPH, MScPM, is Executive Director of RCM Policy and Industry Engagement at EnableComp. He has spent his career at the intersection of healthcare policy and revenue cycle operations, including leadership roles at Orb Health, Wishard Hospital, and Eskenazi Health.
This article summarizes publicly available information from reputable government, news, and industry sources. It is provided for general informational purposes and is not legal, financial, or compliance advice.

FAQs about VA Interoperability

What is revenue cycle management in medical billing?